September 10th

The Postpartum Bulge: Healing Prolapse After Birth With Confidence
Five weeks postpartum. Just when you’re starting to find your rhythm again – there it is. A strange pressure, maybe after a sneeze or lifting your toddler. Maybe you stood up after a rest and felt a heaviness you didn’t expect. Something is different. Off. You reach down and feel a bulge.
This moment – one that’s happened to many – is often the first sign of pelvic organ prolapse (POP). It’s disorienting. Frightening. But also: incredibly common. And there’s good news here. Because the postpartum body is still healing, many people find that their symptoms significantly improve — and often completely resolve — with the right approach, even if some structural changes remain.
What Is Pelvic Organ Prolapse (POP)?
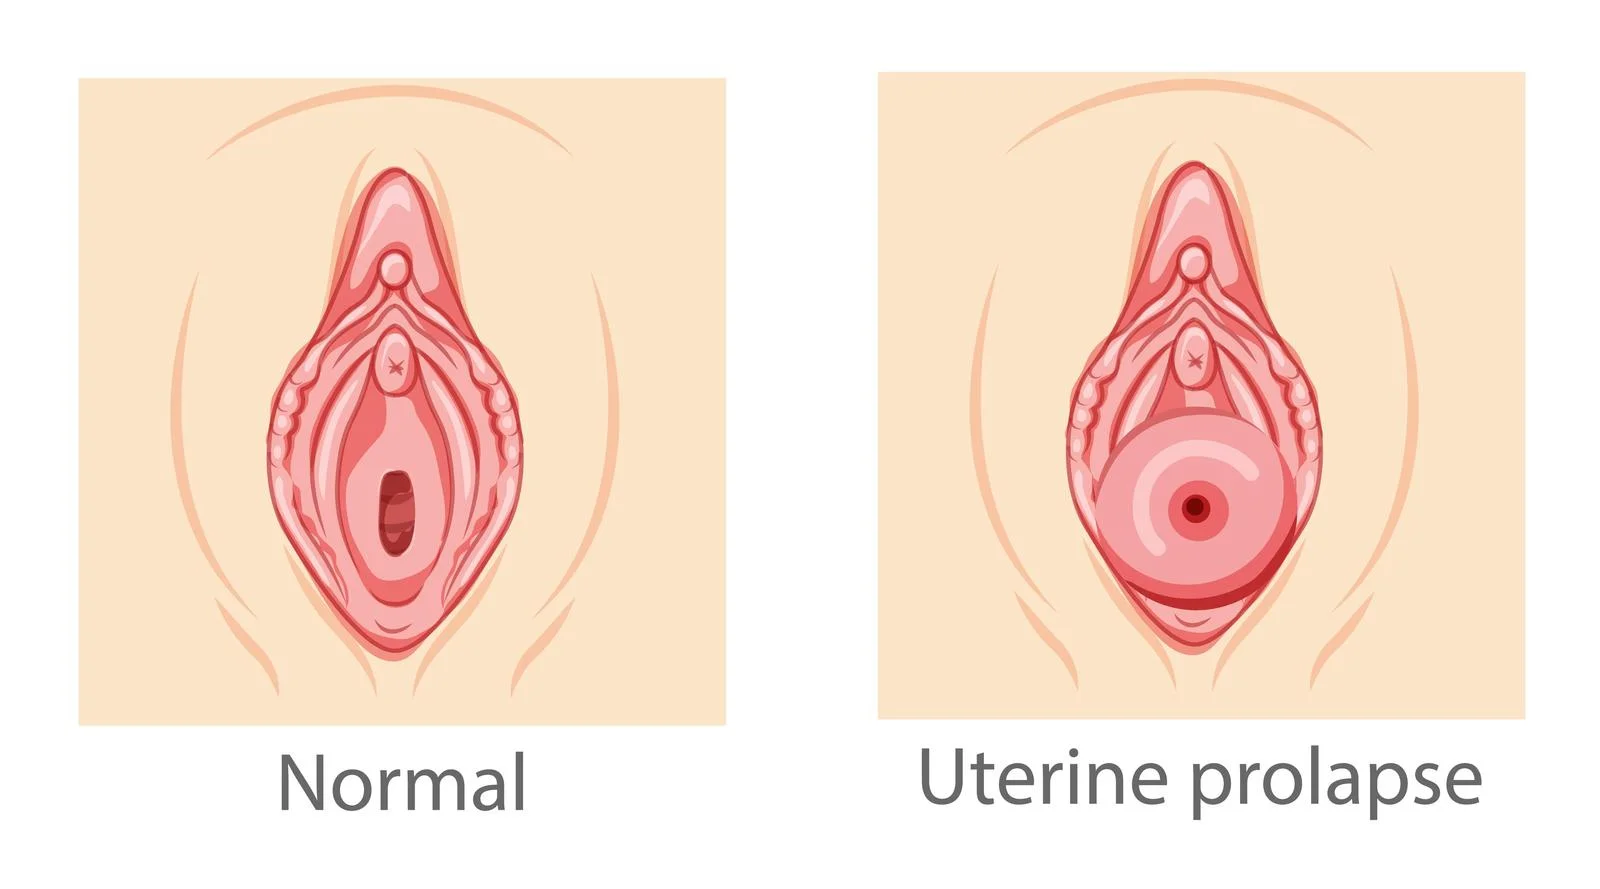
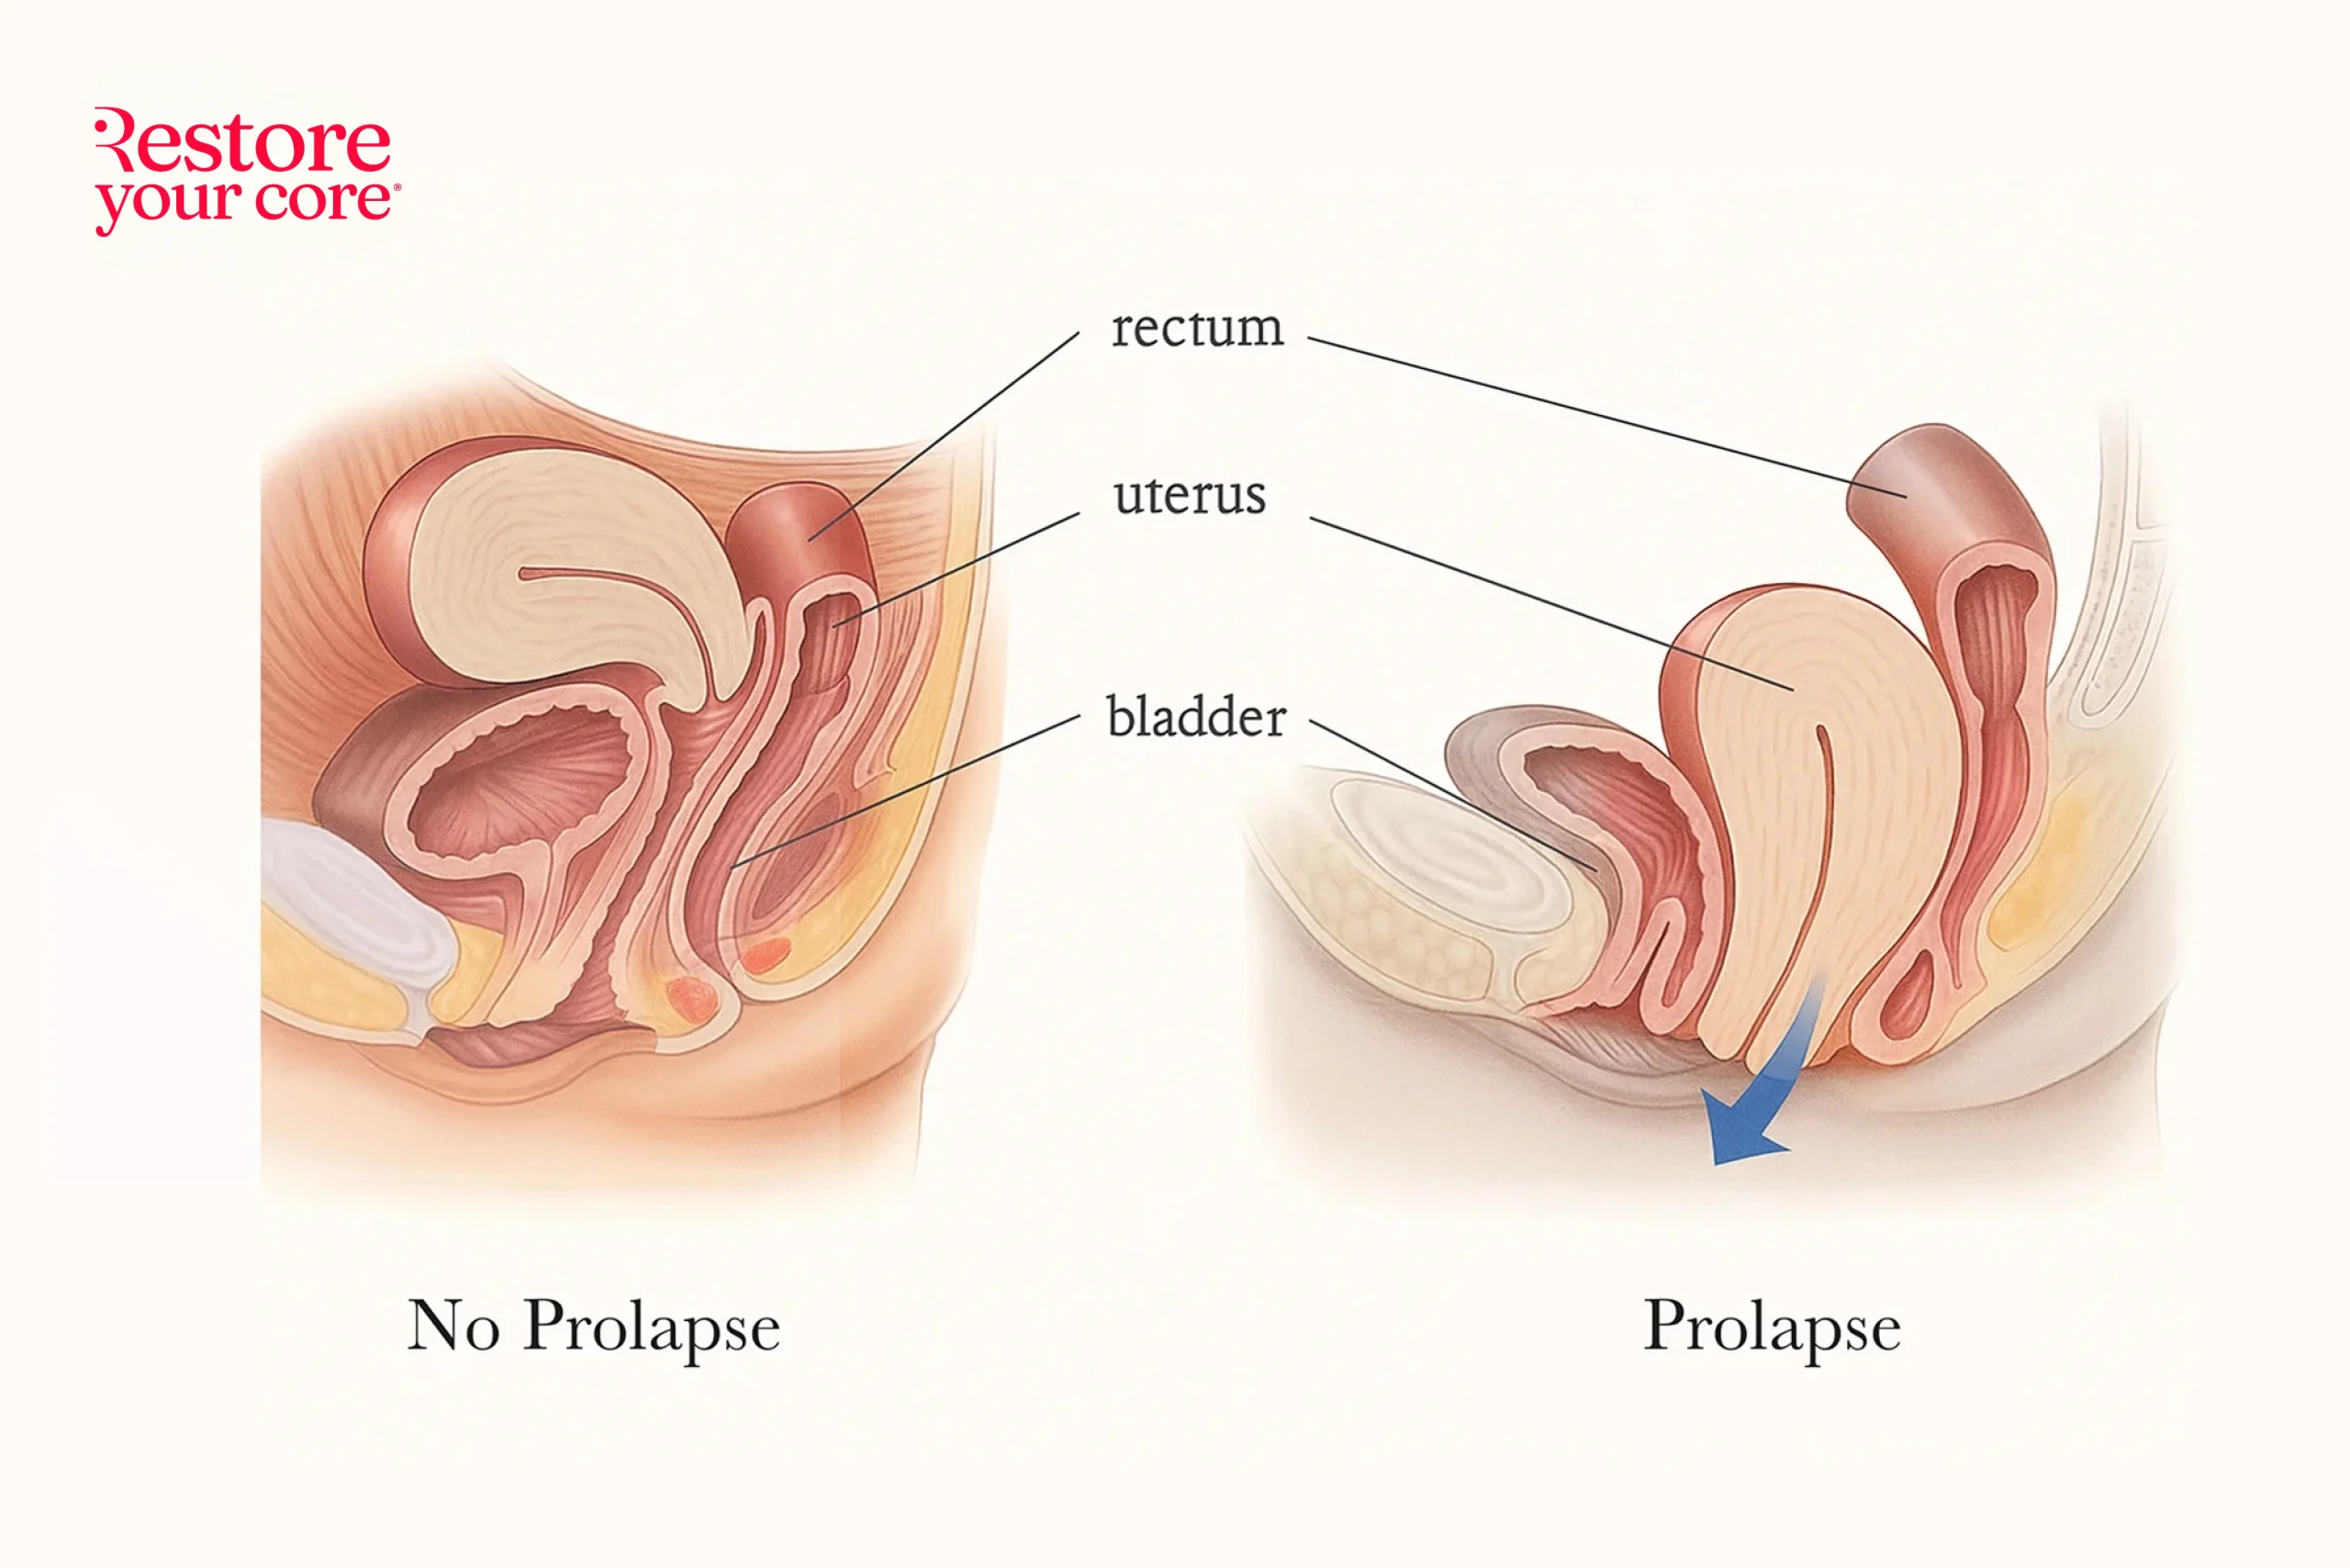
Pelvic organ prolapse (POP) occurs when the muscles and connective tissues that support your pelvic organs – like the bladder, uterus, or rectum – become weakened or stretched. This can allow them to drop and press into the vaginal canal.
It’s a condition rooted in pressure dynamics, tissue resilience, and life experiences (like pregnancy, labor, and daily movement). And understanding it is the first step in changing how we support our bodies.
It’s estimated that up to 50% of people who’ve been pregnant will experience some level of prolapse \[1\]. It’s more common than you think – and far more manageable than you may have been told.
Types of Pelvic Organ Prolapse
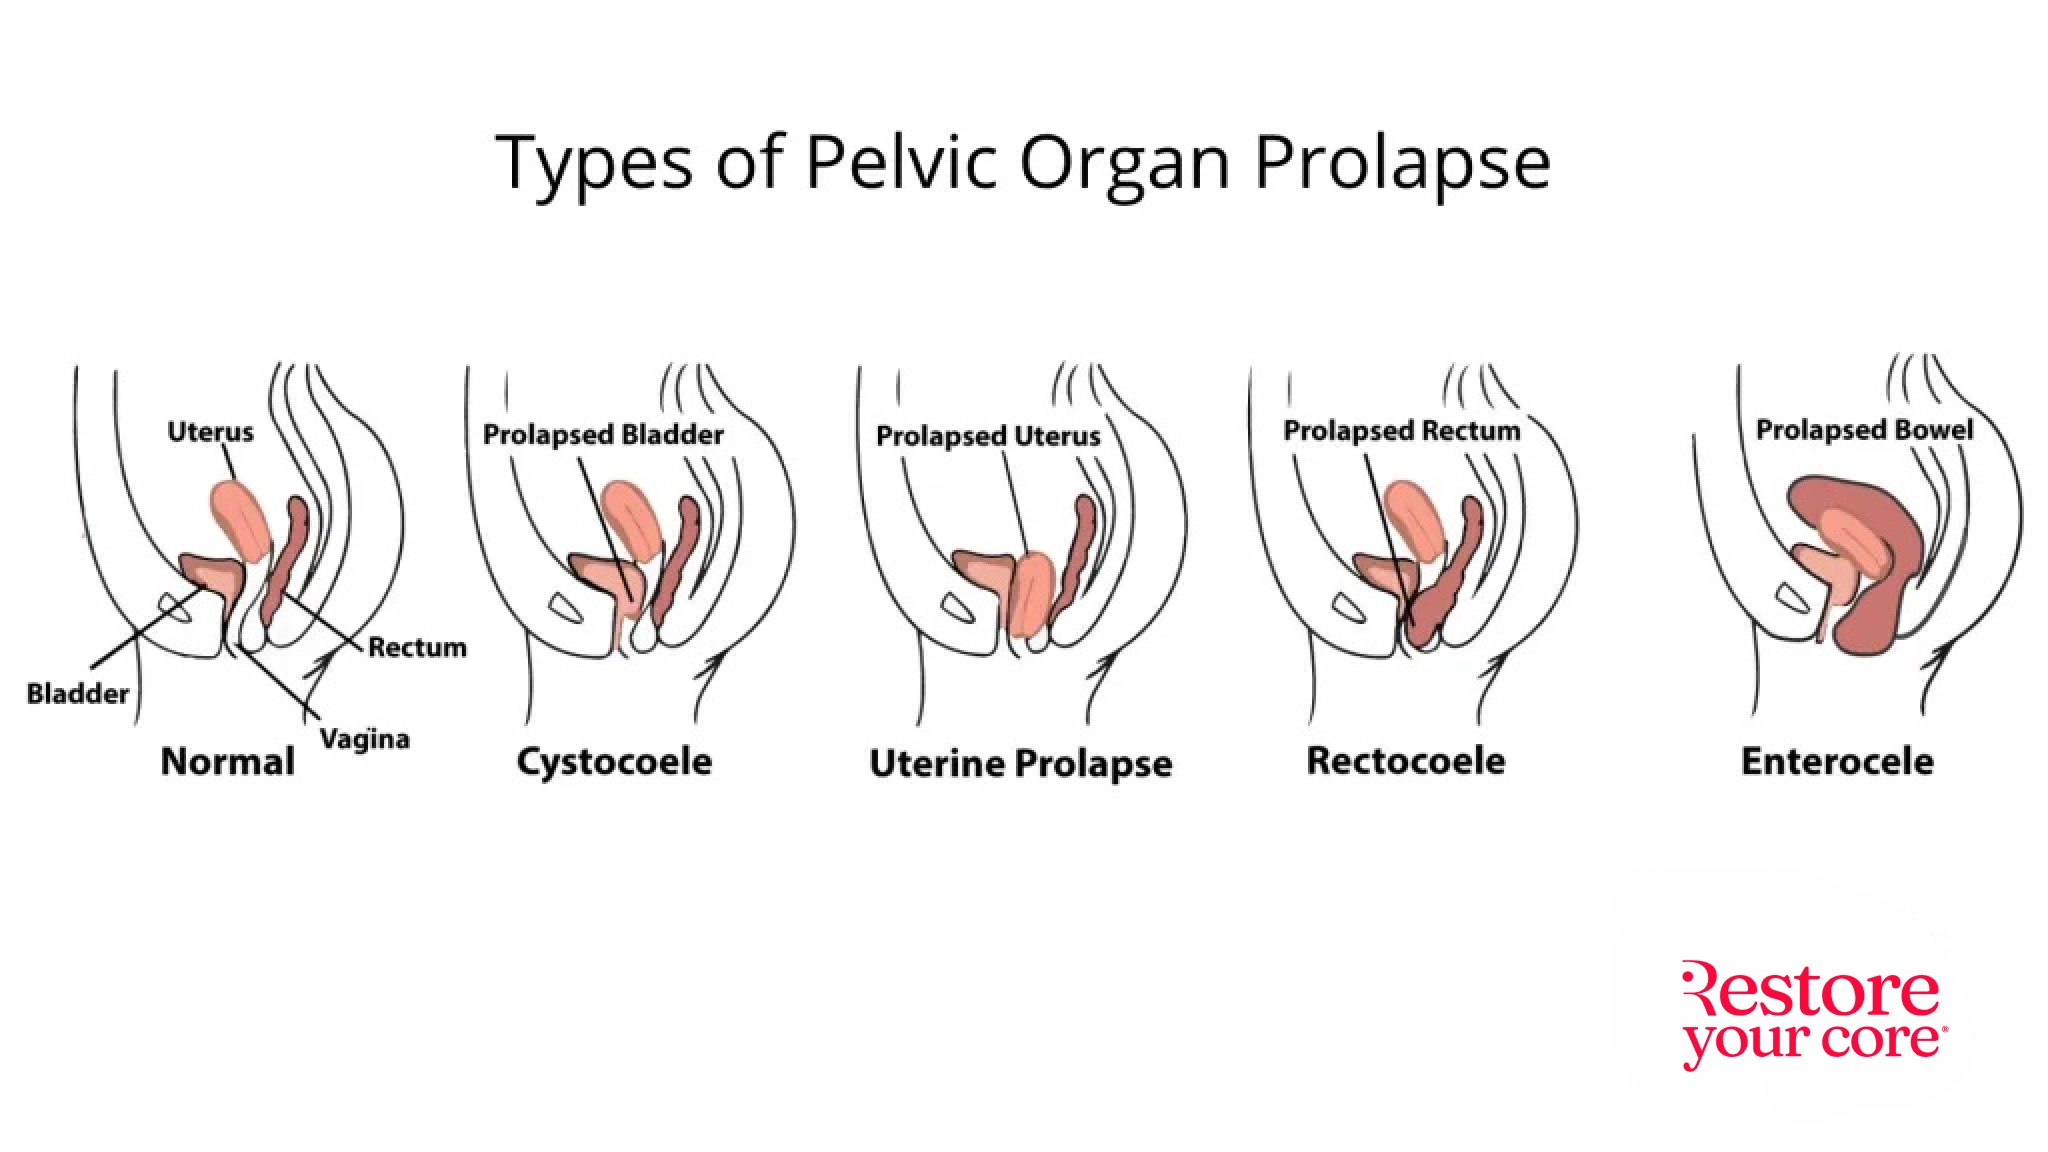
There are several kinds of pelvic organ prolapse, depending on which organ has shifted from its normal position. The three most common types are:
- Cystocele (Bladder Prolapse) – when the bladder bulges into the front vaginal wall.
- Rectocele – when the rectum bulges into the back vaginal wall.
- Uterine Prolapse – when the uterus descends downward into the vaginal canal.
Among these, the most common type after childbirth is bladder prolapse (cystocele), since the front vaginal wall often bears the most pressure and load during pregnancy and delivery.
Sometimes, more than one organ is affected – called multi-compartment prolapse – and this is also quite common postpartum.
Regardless of the type of prolapse, the path to healing is guided by the same principles: managing intra-abdominal pressure and engaging in movements that help restore the optimal function of the core and pelvic floor, so your body feels strong and supported again.
Signs and Symptoms to Watch For
Symptoms of prolapse vary in intensity and may include:
- A sense of pressure or heaviness in the pelvis
- Feeling like there’s a tampon stuck in the vagina
- Feeling like you’re sitting on a small ball
- Noticing a bulge at the vaginal opening
- Urinary incontinence or difficulty fully emptying the bladder
- Constipation or difficulty having a bowel movement
Symptoms often worsen as the day goes on or after activity, and ease with rest.
Severity is staged from 1 (mild) to 4 (severe). However, symptoms don’t always align with the stage. Diagnosis offers insight, but what truly matters is symptom management, which depends on several factors – including strength, movement habits, and breathing mechanics.
What Causes Pelvic Organ Prolapse?
Primary Risk Factors:
- Pregnancy: Changes in pressure systems and hormones, such as relaxin, can affect support tissues.
- Vaginal Birth: Especially after long pushing or the use of forceps/vacuum.
Additional Contributors:
- Being older when you have your first baby
- Giving birth to a large baby
- Aging
- Prior pelvic surgery
- Chronic straining (e.g., constipation)
- Persistent coughing
- High-impact activity
- Heavy lifting
- Genetics or connective tissue differences
Research shows that even one vaginal birth can greatly increase the likelihood of developing pelvic organ prolapse compared with a cesarean birth without labor. One long-term study found that most of the risk happens with that very first vaginal delivery – additional births didn’t seem to raise the risk much further \[2\].
These changes don’t define your future – with proper guidance, mindful movement, and time, your body can regain strength and restore function.
What Healing Looks Like: A Non-Surgical Roadmap
Pelvic organ prolapse doesn’t automatically mean surgery. In fact, many people find meaningful symptom relief and functional improvement through non-surgical strategies – especially when addressed early. Healing is about more than fixing; it’s about restoring function, trust, and support.
Step 1: Get a Proper Assessment
Your first step is an assessment with a physical therapist specializing in pelvic health. They’ll evaluate pelvic muscle strength and function, prolapse stage, and look at how you move and manage intra-abdominal pressure. An accurate diagnosis creates a roadmap for targeted, safe treatment.
Step 2: Begin Personalized Physical Therapy
Pelvic floor physical therapy (PFPT) is a powerful tool – but not all practitioners are created equal. A well-informed pelvic floor therapist can help you:
- Differentiate between a tense and underactive pelvic floor
- Retrain pelvic coordination and breath mechanics
- Improve posture, pressure management, and movement habits
A skilled therapist goes beyond isolated exercises, such as Kegels, to help you understand how your core, breath, and daily movement patterns impact your pelvic health.
Download our guide, *Questions to Ask Your Pelvic Health Provider*, for extra support as you prepare for your first appointment.
Step 3: Integrate a Whole-Body Healing Program
Programs like Restore Your Core® (RYC®) complement physical therapy by offering a structured, whole-body approach to pressure management, core re-patterning, and nervous system regulation.
Rather than targeting symptoms in isolation, RYC® helps you:
- Rebuild functional core and pelvic floor coordination through whole-body, multi-dimensional movement that teaches your system to respond to load and pressure more efficiently.
- Refine postural and breathing patterns so your core and pelvic floor can share the work, reducing excess downward pressure and gripping.
- Re-educate your nervous system to move out of chronic guarding or tension and into patterns of safety, support, and adaptability.
Whether used between PT sessions or as ongoing care, RYC® can guide you to integrate healing into your everyday life.
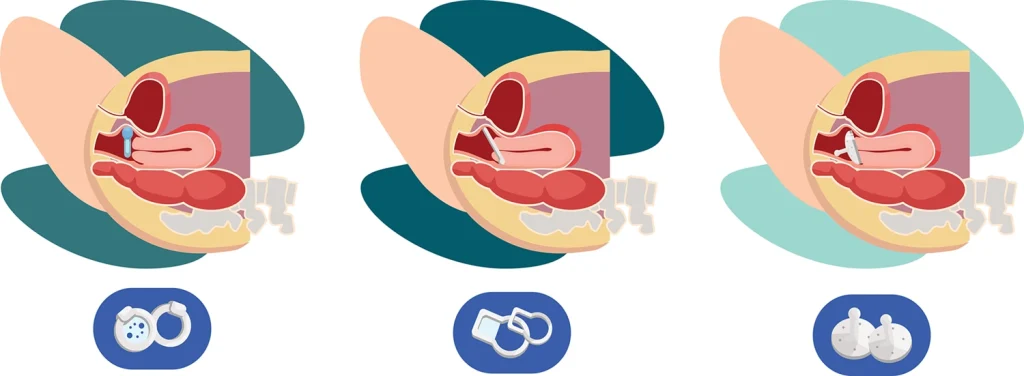
Step 4: Consider a Pessary
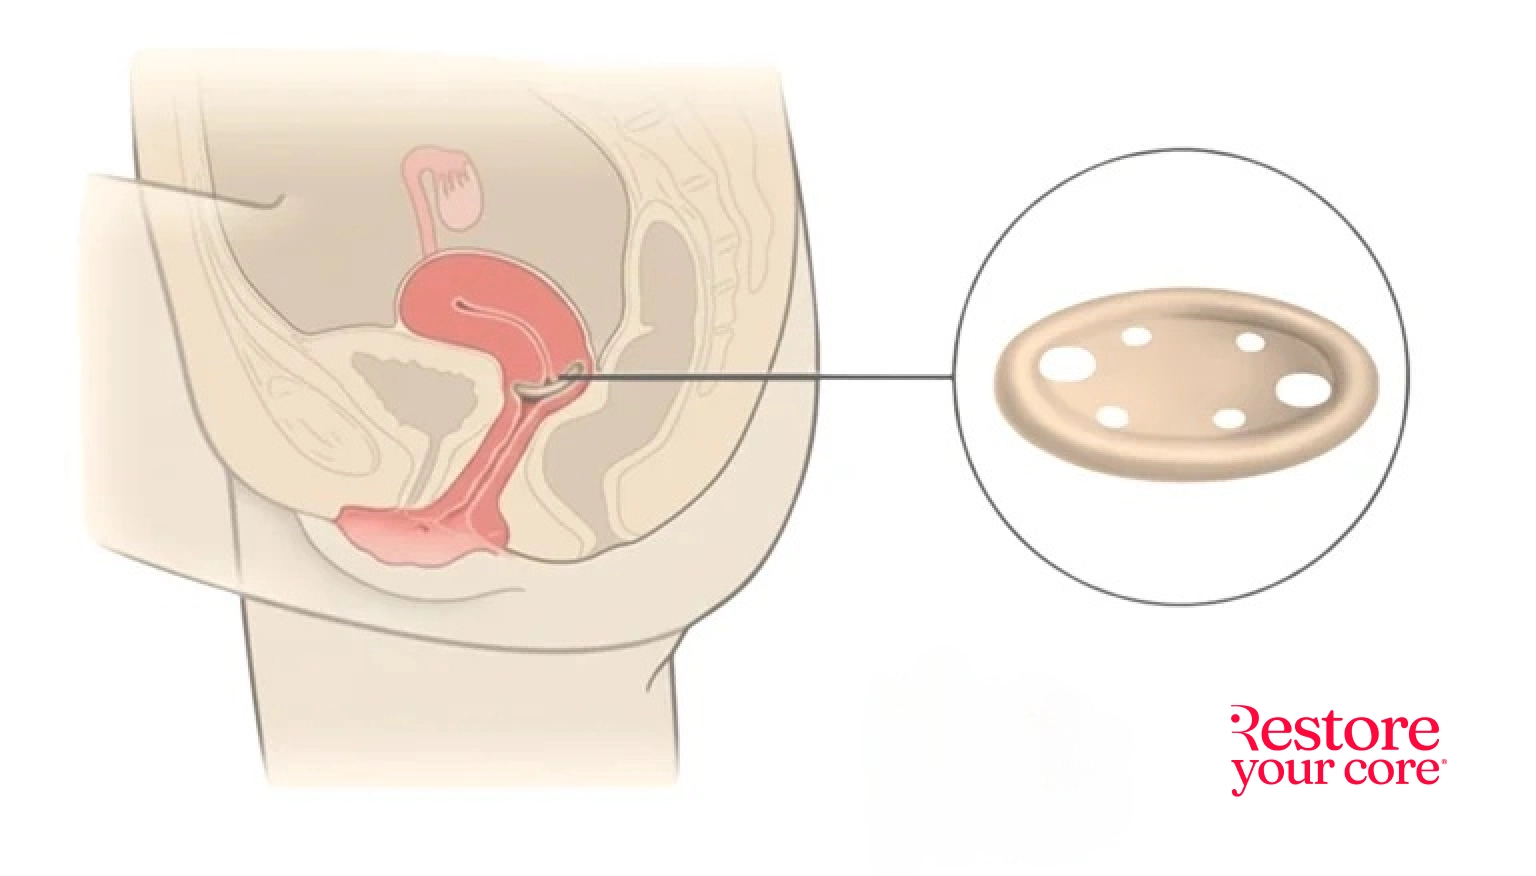
A pessary is a silicone or plastic device fitted by your provider and placed in the vagina to support the prolapsed organs. It acts like a structural assist – lifting and stabilizing without surgery.
Some people use a pessary short-term (during heavier activity days or workouts), while others benefit from regular use. A good fit matters – don’t hesitate to ask for adjustments.
Step 5: Manage Intra-Abdominal Pressure Daily
Your pelvic floor doesn’t act alone. Learning to manage intra-abdominal pressure (IAP) in everyday movement and activities helps to reduce symptoms and support healing:
- Posture awareness: Notice how you stand, staking the ribs over the pelvis helps to distribute pressure more evenly.
- Bowel care: Eat high-fiber foods, hydrate, and avoid straining on the toilet. Use a stool to elevate your feet, and consider rectal support (a finger pressing inside the vagina) if stool gets caught in a rectocele pocket.
- Movement variety: Avoid holding one posture, sitting, or standing for too long. Alternate positions (sitting, standing, walking) to help balance pressure.
- Breath mechanics: Learn how to exhale through effort, especially when lifting, getting out of bed, or standing from a squat.
- Cough or sneeze support: Turn your head to the side, place a hand or forearm across your lower abdomen, lengthen the pelvic floor on the inhale and lift on the exhale.
- Lifting strategy: When lifting children, groceries, or weights, bend your knees, exhale through the effort, and use your legs instead of bearing down.
All of these strategies can be learned and practiced in Restore Your Core® or with your PT to create daily movement patterns that protect and support your pelvic floor.
Living With Prolapse: Movement, Intimacy & Emotional Support

Intimacy
Some people avoid sex for a while – feeling unsure about safety, symptoms, or how their partner will respond. What can help?
- Open, honest conversation
- Learning prolapse doesn’t worsen with sex
- Exploring supportive positions
Movement
Many people safely return to hiking, lifting, and even running after birth. The key is to progress thoughtfully and recognize the signs that your body needs rest or more recovery time:
- A feeling of heaviness, dragging, or increased pressure = time to pause and rest
- Avoid high-impact strain (like running or jumping) until you’ve rebuilt sufficient strength and pelvic support
- Focus on postpartum-informed strength training to restore stability and confidence
- Progress gradually, allowing tissues and connective support to adapt
- Incorporate breath and core coordination to manage pressure effectively
- Expect occasional flare-ups — they’re a normal part of recovery. Use them as feedback to slow down, rest, or adjust your routine
- If symptoms return or worsen, scale back and revisit foundational exercises
And if you want a movement practice that honors your symptoms while rebuilding function, the RYC® 12-Week Program is a safe, intelligent place to begin.
Emotional Health
Give yourself grace. You’re not broken. Your organs are not falling out. Your body is adapting – and you’re listening. That’s healing.
Is Surgery Needed?
Surgery isn’t usually the first step for prolapse care, and many people find meaningful relief through conservative options like pelvic floor therapy, pessaries, and whole-body programs such as Restore Your Core® (RYC®).
That said, surgery can be helpful for more advanced prolapse (Stage 3 or 4) or when symptoms persist despite other treatments. The goal is to restore support by lifting and repairing the affected tissues \[2\].
Mesh repairs are rarely performed now – most surgeries use your own tissue or sutures to strengthen and support the vaginal walls or uterus. If you’re considering surgery, it’s important to see a urogynecologist or pelvic reconstructive specialist who can explain your specific options, expected outcomes, and recovery process.
If you plan to become pregnant again, most providers recommend waiting on surgery until after you’ve finished having children, since pregnancy and birth can stretch or strain repaired tissues.
FAQ
POP occurs when one or more pelvic organs (such as the bladder, rectum, or uterus) drop down from their normal position and bulge into the vagina. This happens due to the weakening, tearing, or stretching of the pelvic floor muscles and supportive tissues/ligaments.
Research indicates that up to around 30 % to 50 % of women who have given birth experience some degree of pelvic organ prolapse (POP) in the postpartum period, although the vast majority of these cases are mild and asymptomatic [3].
Symptoms of prolapse can appear immediately after childbirth, but it’s also very common for them to become noticeable weeks to months later, especially as postpartum swelling decreases and normal activity levels increase. Some women don’t notice symptoms until they resume exercise, lift heavier loads, or return to work. In some cases, a prolapse that began with childbirth doesn’t become symptomatic until perimenopause, when decreasing hormone levels affect the pelvic floor’s ability to support the organs.
The most common symptoms are related to sensation and function: A feeling of heaviness, dragging, discomfort, or pressure in the pelvis or vagina. The sensation of seeing or feeling a lump/bulge inside (or coming out of) the vagina. Difficulty emptying the bladder (urinary urgency or incontinence) or trouble fully eliminating stool (constipation).
Vaginal birth is strongly associated with an increased risk of POP compared to cesarean delivery without labor. The highest risk is linked to operative vaginal birth (using forceps or vacuum extraction), which can increase the odds of prolapse (to or beyond the hymen) by almost 8-fold compared to cesarean before labor. Longer labors and extended periods of pushing can place additional strain on the pelvic floor, potentially affecting its ability to provide optimal support.
The first-line approach for managing POP is typically conservative: Pelvic Floor Physical Therapy (PFT): Working with a pelvic floor specialist is highly recommended to learn techniques for managing intra-abdominal pressure, with exercises to strengthen supporting muscles and relieve symptoms. Not everyone is prescribed Kegels, but if it is recommended for you, your provider will ensure you’re doing them effectively. Pessaries: A small silicone or plastic device can be inserted into the vagina to physically support the organs and decrease symptoms. Lifestyle Changes: This includes preventing constipation by increasing fiber and fluids, maintaining a healthy weight, avoiding heavy lifting, and treating chronic coughs. The Restore Your Core® program is an excellent complement to this approach, especially if you’re looking for a structured, body-literate way to retrain your core and movement patterns.
References
- Bugge, C., Adams, E. J., Gopinath, D., Stewart, F., Dembinsky, M., Sobiesuo, P., & Kearney, R. (2020). Pessaries (mechanical devices) for managing pelvic organ prolapse in women. Cochrane Database of
- Donnelly, M. J., Powell-Morgan, S., Olsen, A. L., & Nygaard, I. E. (2004). Vaginal pessaries for the management of stress and mixed urinary incontinence. International Urogynecology Journal and Pelvic
- Clemons, J. L., Aguilar, V. C., Tillinghast, T. A., Jackson, N. D., & Myers, D. L. (2004). Patient satisfaction and changes in prolapse and urinary symptoms in women who were fitted successfully with
- Fernando, R. J., Thakar, R., Sultan, A. H., Shah, S. M., & Jones, P. W. (2006). Effect of vaginal pessaries on symptoms associated with pelvic organ prolapse. Obstetrics & Gynecology, 108(1), 93–99.
- Al-Shaikh, G., Syed, S., Osman, S., Bogis, A., & Al-Badr, A. (2018). Pessary use in stress urinary incontinence: A review of advantages, complications, patient satisfaction, and quality of life. Inter
- Pires, T., Pires, P., Moreira, H., & Viana, R. (2020). Prevalence of urinary incontinence in high-impact sport athletes: A systematic review and meta-analysis. Journal of Human Kinetics, 73, 279–288.
- Farrell, S. A., Baydock, S., Amir, B., & Fanning, C. (2007). Effectiveness of a new self-positioning pessary for the management of urinary incontinence in women. American Journal of Obstetrics and Gyn